
Keratoconus vs Keratoglobus: How They Differ

Introduction: Keratoconus vs. Keratoglobus
Two conditions that often confuse patients and even general practitioners because of their similar names are keratoconus and keratoglobus. Both are classified as corneal ectasias, meaning diseases where the cornea becomes abnormally thin and distorted. These conditions disrupt the normal, transparent, dome-like shape of the cornea, causing light to scatter as it enters the eye and thereby reducing vision quality.
While keratoconus is a relatively common disorder, keratoglobus is considered a rarer condition. (A third member of the ectasia family, pellucid marginal degeneration, is compared with keratoconus separately.) The difference lies not only in the patterns of corneal thinning but also in the severity of complications, management options, and surgical strategies. Understanding these distinctions is essential for accurate diagnosis, effective treatment, and improving the best corrected visual acuity of affected patients.

Clinical Findings and Ocular Signs
The ocular signs of keratoconus and keratoglobus can overlap, but they also present distinct features that guide ophthalmologists in diagnosis.
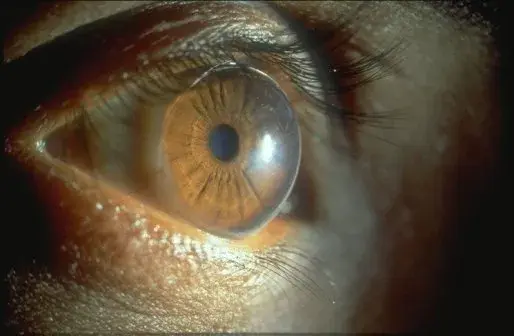
In keratoconus, patients typically present in their teens or early adulthood with increasing blurred vision, irregular astigmatism, and frequent changes in their spectacle prescription. Examination often reveals a conical protrusion of the cornea, thinning at the apex, and distortion of the K values on corneal topography. Fleischer’s ring, Vogt’s striae, and scissoring reflex on retinoscopy are hallmark findings.
In contrast, keratoglobus involves more generalised and diffuse thinning across the entire cornea, characterised by a globular protrusion rather than a cone. Because of the thin cornea, these patients are at higher risk of corneal perforation even after trivial trauma or minimal trauma, making protective glasses a crucial part of management. Additional findings may include blue sclera, bilateral keratoglobus, and associated connective tissue disorders such as Marfan syndrome.
Both diseases can lead to high myopia, irregular astigmatism, and reduced vision that does not fully correct with glasses. Many patients require contact lens insertion, often with a scleral contact lens, to achieve functional refractive correction.
Corneal Shape and Corneal Thinning in Both Conditions
The shape of the cornea is the most obvious clinical difference between the two disorders.
Keratoconus:
Localised thinning results in a cone-shaped protrusion of the cornea, typically located inferiorly or centrally. This irregular curvature produces progressive visual distortion, glare, and image ghosting. Over time, the disease stabilises, but some patients progress rapidly and require early surgical management.
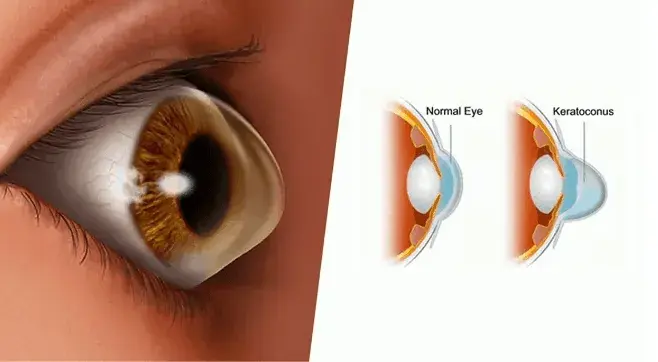
Keratoglobus:
Instead of a cone, the entire cornea becomes thin and takes on a rounded or globular protrusion. The extreme thinning makes the cornea fragile, increasing the risk of rupture and acute corneal hydrops. Unlike keratoconus, this condition is often present from birth or early childhood and may be associated with acquired keratoglobus in later life following chronic inflammatory disease.
In both cases, corneal topography plays a vital role in diagnosis and monitoring disease progression. Precise mapping of the corneal curvature helps ophthalmologists decide between conservative treatment, new surgical techniques, or more traditional surgical procedures such as penetrating keratoplasty.
Progression, Risk Factors, and Associated Conditions
Keratoconus usually appears in adolescence and progresses over 10–20 years before stabilising. Risk factors include eye rubbing, family history, and associated systemic or ocular conditions. Vernal keratoconjunctivitis is strongly associated, as persistent eye rubbing and chronic inflammation accelerate corneal weakening. Similarly, chronic marginal blepharitis and poorly managed allergic eye disease can worsen corneal thinning.
Keratoglobus, however, is less predictable. It often manifests early in life and may progress slowly, but carries a higher risk of complications such as corneal perforation. Some patients develop acquired keratoglobus in adulthood as a result of inflammatory disorders. Systemic connective tissue disorders, such as Marfan syndrome and blue sclera syndrome, are often linked with bilateral presentation.
Both diseases carry the risk of glaucoma, retinal detachment, and reduced best corrected visual acuity if left unmanaged. Case reports in leading journals, such as the British Journal of Ophthalmology and Archives of Ophthalmology, have documented severe cases of bilateral disease, acute hydrops, and even vision loss in one eye or the same patient, affecting the left eye and right eye at different times.

Acute Hydrops and Complications
One of the most feared complications in corneal ectasias is acute hydrops. This occurs when Descemet’s membrane ruptures, allowing fluid from the anterior chamber to flood into the cornea. The result is sudden, painful swelling, dramatic loss of vision, and prolonged resolution time that can extend to weeks or months.
In keratoconus, acute hydrops may occur spontaneously, but it is less common. In keratoglobus, due to the thin cornea and diffuse thinning, the risk is significantly higher, sometimes triggered by even trivial trauma. The disease can lead to recurrent hydrops, corneal scarring, and a permanent reduction in best-corrected visual acuity.
Management often includes bandage contact lenses, hypertonic saline, and, in some cases, intracameral injection of perfluoropropane gas to accelerate recovery. However, in keratoglobus patients, surgical repair may be needed due to extreme thinning.

How Treatment Differs Between the Two Conditions
The most important practical difference between the two conditions is how much the pattern of corneal thinning limits treatment. In keratoconus, the thinning is localised, so there is usually enough healthy tissue to stabilise the cornea with corneal cross-linking, and the full range of options is covered on our keratoconus treatment page.
Keratoglobus is far harder to treat surgically. Because the thinning runs from limbus to limbus, cross-linking is rarely safe, and a standard graft has little solid peripheral tissue to anchor to. Techniques such as a peripheral intralamellar tuck or large lamellar grafts are sometimes used instead, and protective glasses are essential because even trivial trauma can perforate the fragile cornea. Where grafting is needed, the approaches are explained on our corneal transplants page.
Keratoconus and Keratoglobus – Diagnosis and Treatment Outlook
Although keratoconus and keratoglobus share overlapping features, they remain distinct conditions with unique diagnostic challenges and treatment pathways. Keratoconus is more prevalent, with well-established therapies including corneal cross-linking and scleral contact lens fitting. Keratoglobus, being a rarer condition, demands heightened caution due to its extreme thinning, higher risk of corneal perforation, and limited options for safe surgical correction.
Recent studies in Arch Ophthalmol, Br J Ophthalmol, and institutional reports from Prasad Eye Institute highlight ongoing research into new surgical techniques, improved surgical management, and safer alternative surgical procedures for these complex diseases.
For patients, the key lies in early diagnosis, regular follow-up, and individualised management options tailored to their specific needs. For ophthalmologists, the challenge remains in balancing conservative therapy with advanced surgical procedures and minimising risks, such as glaucoma, retinal detachment, and graft failure.
Ultimately, understanding the differences between these two corneal ectasias ensures better treatment, improved vision, and greater quality of life for patients. As research continues, novel interventions promise safer and more effective ways to manage both keratoconus and keratoglobus in the future.
